Rebuilding a severely damaged or deformed leg is one of the most demanding challenges in orthopedic surgery. Every bone has its own geometry, and when fractures, infections, or congenital deformities distort the anatomy of the femur, tibia, or heel, the mental reconstruction a surgeon performs from flat two-dimensional CT slices can only go so far. A new descriptive case series published in the journal 3D Printing in Medicine by researchers at Universidad de los Andes and Fundación Cardioinfantil in Bogotá, Colombia, documents how a hospital team has woven three-dimensional imaging, modeling, and printing directly into preoperative planning for four complex lower extremity reconstructions, and what the surgeons who used these tools thought of the experience.
The study, led by Ines Maria Fernandez-Calderon and colleagues at the university’s Department of Biomedical Engineering and the hospital’s Center for 3D Modeling and Printing, was explicitly framed as a demonstration rather than a trial. The authors set out to show the variety of ways their department has deployed 3D technologies to manage difficult lower limb cases, and to capture the perceptions of the operating surgeons through questionnaires. Their conclusion is measured but firm: three-dimensional technologies are particularly advantageous in complex cases that require precise, individualized solutions, especially when conventional methods are insufficient because the anatomy is challenging or the deformity severe.
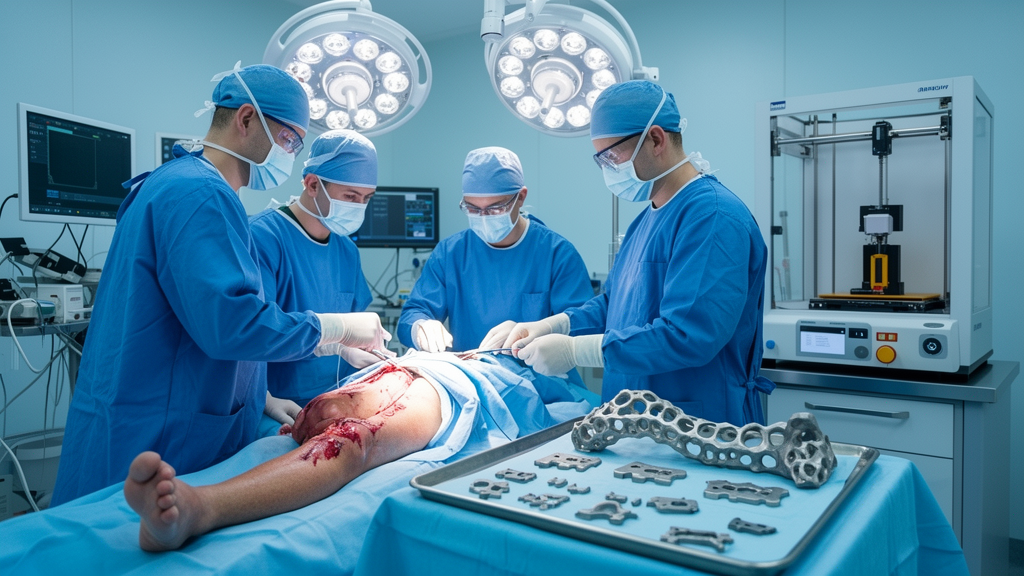
The technical pipeline behind such planning is worth understanding in detail. It typically begins with computed tomography, whose stacked cross-sectional images are converted into digital three-dimensional models of the patient’s bones. Those models can then be manipulated in software: surgeons and biomedical engineers can rotate the anatomy, measure angles that matter for limb alignment, simulate osteotomy cuts, and test how an implant or graft will fit before anyone touches a scalpel. Selected components are then physically fabricated, often by fused deposition modeling, a 3D printing method that builds objects layer by layer from thermoplastic material such as polylactic acid. The result can be a patient-specific instrument, a physical anatomical model for rehearsal, or a custom-shaped graft or spacer matched to a single patient’s skeleton.
That precision matters because limb reconstruction lives and dies by angles. The authors’ abbreviation list hints at the measurements involved: the mechanical lateral distal femoral angle, the posterior distal femoral angle, and the medial lateral tibial angle are all parameters that determine whether a leg will bear weight in a straight, mechanically sound line after surgery. When a surgeon performs a femoral or tibial osteotomy, the planned correction of these angles must be translated into real bone cuts, and small deviations can compound into lasting misalignment. Patient-specific instrumentation, printed to sit on the patient’s unique bone surface, is designed to carry those planned angles from the digital plan to the operating field.
The four cases presented in the series span the range of what 3D technologies can contribute. Two were pediatric deformity corrections: a 17-year-old female who underwent multiple femoral osteotomies with the aid of custom 3D-printed guides, and a 7-year-old female who underwent a tibial osteotomy guided the same way. In both, the printed guides served as physical embodiments of the surgical plan, positioning cuts so that the intended angular corrections could be achieved in growing bones where every millimeter of alignment influences future development.
The third case moved beyond guides into the shaping of biological material. A 48-year-old female required a calcaneal allograft, meaning donor bone intended to reconstruct the calcaneus, the heel bone that absorbs enormous loads with every step. Rather than trimming the allograft freehand, the team used 3D modeling to shape it, matching the graft’s contours to the defect it needed to fill. The heel is an anatomically unforgiving target: its complex, irregular geometry makes it notoriously difficult to reconstruct from standard implants or generic templates, which is precisely the situation the authors identify as the best fit for 3D assistance.
The fourth case illustrates a different role for the technology entirely. A 21-year-old male was treated with a 3D-modeled tibial spacer as part of the Masquelet technique, a staged reconstruction strategy used for significant segmental bone loss. In the Masquelet approach, a first procedure places a cement spacer in the bone defect, which induces the formation of a vascularized membrane around it; in a second stage, the spacer is removed and the membrane-lined cavity is filled with bone graft. Modeling the spacer in three dimensions before fabrication allows it to be tailored to the patient’s tibial defect, a step the Bogotá team integrated into their preoperative workflow.
Surgeons’ perceptions were formally evaluated through questionnaires, and the series reports that the tools enhanced the team’s understanding of patient-specific anatomy and improved surgical outcomes in these cases. The authors are careful, however, not to oversell the approach. They note that not every case necessitates three-dimensional technologies, and that its application is most appropriate when conventional methods fall short, particularly in anatomically challenging situations or severe deformities. Routine fractures and straightforward procedures, in other words, may not justify the added modeling time, cost, and coordination that a 3D workflow requires.
What emerges most clearly from the study is that the technology is only half of the story. The authors emphasize that the success of these interventions depends on a multidisciplinary approach, combining the expertise of engineers and medical professionals. Their own authorship reflects that model: biomedical engineers from Universidad de los Andes worked alongside the hospital’s orthopedics service, radiology and diagnostic imaging department, and the Center for 3D Modeling and Printing, with one co-author, Javier Navarro-Rueda, also affiliated with the University of Minnesota’s Visible Heart Laboratories. The modeling and printing center itself is funded by the Colombian Ministry of Science, MinCiencias, under contract 744-2021, an indication that national science agencies are investing in hospital-based 3D capabilities as clinical infrastructure rather than laboratory curiosities.
The work was conducted in accordance with the Declaration of Helsinki, with institutional review board and ethics committee approval from Fundación Cardioinfantil, and informed consent obtained from all patients and, for the pediatric cases, from their parents or legal guardians. For a field watching patient-specific instrumentation and 3D printing move steadily from novelty toward standard of care, the Bogotá series offers a practical template: begin with CT data, build a digital twin of the patient’s anatomy, plan the correction collaboratively with engineers, print the guides, models, grafts, or spacers that carry the plan into the operating room, and reserve the whole apparatus for the cases where it genuinely changes what is possible. The authors’ recommendation to other departments is straightforward: consider integrating three-dimensional technologies as an adjunct in the treatment of complex lower extremity reconstruction, because the same digital pipeline that lets a surgeon rehearse a femoral osteotomy on a 17-year-old’s printed femur can reshape a heel graft, design a Masquelet spacer, and turn two-dimensional scans into three-dimensional surgical confidence.
Subject of Research: Use of 3D printing and modeling technologies for preoperative planning in complex lower extremity reconstructive surgery
Article Title: Integration of 3D technologies in preoperative planning for complex lower extremity reconstructions: a descriptive case series study
Article References: Fernandez-Calderon, I. M., Pérez-Cualtán, C. E., Torres-Gómez, D., Brilla, M. A. R., Castro-Páez, C., Pérez, J. M., Rodríguez-Torres, O., Briceño, J. C., & Navarro-Rueda, J. (2026). Integration of 3D technologies in preoperative planning for complex lower extremity reconstructions: a descriptive case series study. 3D Printing in Medicine. https://doi.org/10.1186/s41205-026-00349-3
Image Credits: AI Generated
DOI: 10.1186/s41205-026-00349-3
Keywords: 3D printing, lower limb reconstruction, orthopedic surgery, patient-specific instrumentation, osteotomy, Masquelet technique, surgical planning, computed tomography, biomedical engineering, reconstructive surgery, calcaneal allograft, preoperative planning
Cite Scienmag News
Ophelia Keating. (October 8, 2026). 3D-Printed Tools Help Surgeons Rebuild Complex Leg Injuries with New Precision. Scienmag. https://scienmag.com/3d-printed-tools-help-surgeons-rebuild-complex-leg-injuries-with-new-precision/
Ophelia Keating. "3D-Printed Tools Help Surgeons Rebuild Complex Leg Injuries with New Precision." Scienmag, 8 October 2026, https://scienmag.com/3d-printed-tools-help-surgeons-rebuild-complex-leg-injuries-with-new-precision/. Accessed 8 October 2026.
Ophelia Keating. "3D-Printed Tools Help Surgeons Rebuild Complex Leg Injuries with New Precision." Scienmag. October 8, 2026. https://scienmag.com/3d-printed-tools-help-surgeons-rebuild-complex-leg-injuries-with-new-precision/