For the roughly 40.1 million people in the United States living with diagnosed or undiagnosed diabetes, about 12 percent of the population, the hardest glucose numbers to conquer are often the ones that appear right after dinner. A new narrative review published in Frontiers in Endocrinolology by Janet B. McGill of Washington University, Irl B. Hirsch of the University of Washington, Carol J. Levy of the Icahn School of Medicine at Mount Sinai, Eda Cengiz of the University of California, San Francisco, Grazia Aleppo of Northwestern University, and Anders L. Carlson of the International Diabetes Center argues that the postprandial glucose rise is a critical and frequently neglected component of overall glycemic management. All individuals with type 1 diabetes require physiologic insulin replacement covering both basal and prandial needs, and among adults with type 2 diabetes in 2022, approximately 30 percent required insulin therapy. Yet even with modern devices, many struggle to reach the American Diabetes Association goal of hemoglobin A1C below 7 percent and more than 70 percent of daily time within the glucose range of 70 to 180 mg/dL.
The biology behind the postprandial spike is complex and varies from person to person. In type 2 diabetes, the loss of first-phase insulin secretion is a hallmark, producing elevated and prolonged hyperglycemia after eating. Impaired beta-cell function means inadequate insulin secretion fails to suppress glucagon release from pancreatic alpha-cells, which drives dysregulated hepatic glucose production through increased gluconeogenesis and glycogenolysis, dumping extra glucose into the bloodstream precisely when it is least wanted. Insulin resistance in the liver and peripheral tissues compounds the problem. The review also highlights the adipokine leptin: people with type 2 diabetes are effectively leptin resistant, which increases appetite and dysregulates lipid storage while raising hepatic glucose output. Together, overproduction of glucose from the liver and impaired uptake by fat and muscle disrupt glucose homeostasis and ultimately contribute to the development of type 2 diabetes itself.
The liver emerges as a central player in establishing postprandial glucose levels. After a meal, it shifts from a fasting state of glucose production to glucose absorption and storage as glycogen, and it is estimated to dispose of approximately 60 to 65 percent of an oral glucose load. In chronic hyperglycemia, glycogen metabolism becomes altered, with reduced postprandial glycogen synthesis prolonging the duration of hyperglycemia. In type 2 diabetes, postprandial hyperglycemia signals impaired suppression of endogenous glucose production, a primary function of insulin; in type 1 diabetes with unmanaged postprandial glucose, suppression rates and glycogen metabolism are similarly disturbed. Genetic variation may contribute to interindividual differences through effects on intestinal glucose absorption and pathways governing insulin sensitivity and secretion, although pharmacogenetic findings, including differential responses to metformin, still require validation before they can guide individualized treatment selection.
The stakes extend beyond daily numbers. Postprandial hyperglycemia is a direct and independent risk factor for cardiovascular disease, possibly exerting harmful effects through the production of free radicals, although the precise mechanisms remain unclear. Inadequate postprandial management, commonly associated with higher A1C levels, increases glucose exposure and contributes to microvascular complications such as nephropathy and retinopathy and macrovascular complications including cardiovascular disease and stroke, both major causes of mortality. In healthy individuals with normoglycemia, the postprandial peak typically occurs about 30 minutes after a meal, is usually below 120 mg/dL, and rarely exceeds 140 mg/dL. In people with type 2 diabetes, the peak arrives more than 60 minutes after eating, a rightward shift that reflects reduced first-phase insulin secretion and a reduced incretin effect, leaving hepatic glucose output poorly controlled and muscle glucose uptake less efficient.
Continuous glucose monitoring has transformed how these excursions are seen and understood. CGM metrics provide retrospective averages of interstitial glucose over 24 hours but do not by themselves differentiate fasting from postprandial values, so interrogation of daily tracings is needed. Time in tight range, the percentage of time glucose falls within 70 to 140 mg/dL, mirrors normal physiology: one study in individuals without diabetes found a median of 96 percent time in tight range, supporting fasting values near 100 mg/dL and postprandial peaks below 140 mg/dL. Notably, postprandial elevations have been observed in about 39 percent of patients with otherwise optimal A1C values. Current guidelines recommend assessing postprandial glucose when A1C remains above target despite preprandial goals, measuring 1 to 2 hours after the start of a meal, with the ADA endorsing a peak below 180 mg/dL and AACE recommending a stricter 2-hour goal below 140 mg/dL to achieve an A1C of 6.5 percent or less.
CGM-connected systems also expose the behavioral pitfalls that sabotage mealtime control: delayed or missed bolus dosing, imprecise carbohydrate counting, and reliance on postmeal corrections, which produce high postprandial peaks, larger areas under the glucose curve, and later hypoglycemia from insulin dose stacking. Carbohydrates remain the primary nutrient affecting the postprandial rise, and exact carbohydrate counting, using an insulin-to-carbohydrate ratio to match each bolus to the grams consumed, has measurable benefits. In one study of 40 participants with type 1 diabetes, peak glucose improved from 241 mg/dL before carbohydrate counting to 149 mg/dL afterward, and median A1C fell from 8.0 percent on standard insulin regimens to 7.3 percent with flexible dosing, without increasing hypoglycemia risk. Flexible dosing simplifies the approach by adjusting boluses to meal size and premeal glucose rather than exact carbohydrate grams, though human error and the burden of manual counting remain limitations.
Meal composition and timing offer additional levers. Eating carbohydrates last in a meal, after protein or vegetables, may aid in regulating the postprandial rise, and regular aerobic exercise improves glycemic management in adults with type 2 diabetes, with effects maximized when exercise occurs in the postprandial period. Protein intake enhances incretin effects and insulin secretion, while fats consumed alongside carbohydrates slow gastric emptying and delay glucose release into the blood. Noninsulin medications add further options for type 2 diabetes: alpha-glucosidase inhibitors delay carbohydrate absorption, GLP-1 receptor agonists augment glucose-dependent insulin secretion, suppress glucagon, and slow gastric emptying, and SGLT2 inhibitors increase urinary glucose excretion. The incretin mimetics and SGLT2 inhibitors are particularly effective at lowering postprandial glucose without causing hypoglycemia, whereas meglitinides and sulfonylureas, which stimulate insulin secretion, carry higher hypoglycemia risk.
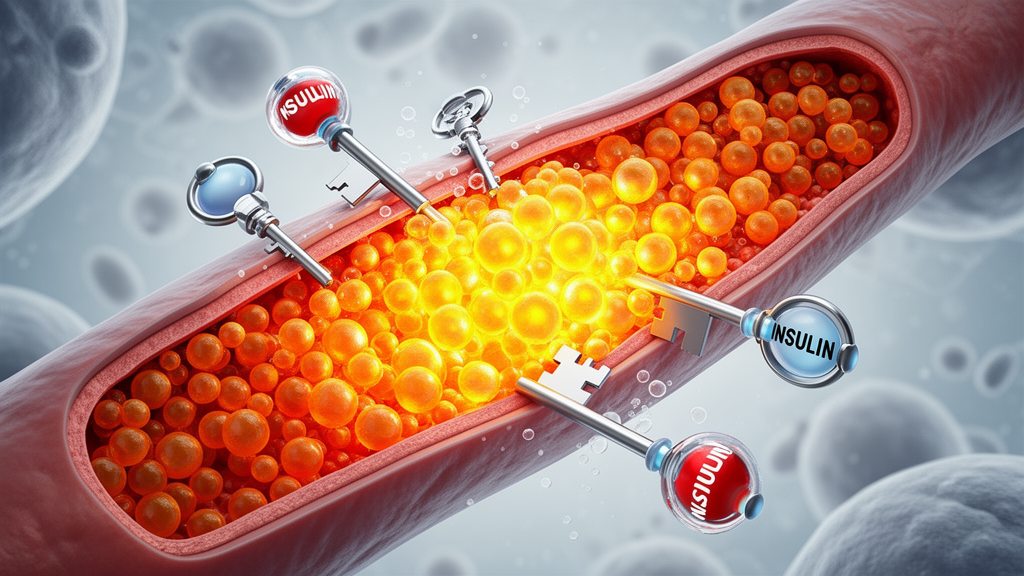
For insulin itself, kinetics are everything. Short-acting injectable insulin has an onset of 30 to 60 minutes with peak glucose-lowering action between 80 and 120 minutes after injection; rapid-acting analogs can take up to 30 minutes for a measurable effect and up to an hour to reach maximum concentrations, remaining active for up to 5 hours. This mismatch with nutrient absorption means insulin often must be administered 15 to 20 minutes before a meal, and earlier still when premeal glucose is high or the CGM trend arrow is uptrending. Repeated injections into the same skin region cause lipohypertrophy, reducing the rate and amount of insulin absorption and deteriorating postprandial control, so site rotation education should be reinforced. Technosphere inhaled insulin offers an ultra-fast onset and shorter duration, concentrating its effects for roughly 3 hours after a meal and more closely resembling physiologic prandial insulin release; postprandial levels were lower without increased hypoglycemia risk in type 1 diabetes compared with injected rapid-acting insulin. However, it is contraindicated in chronic lung disease because of acute bronchospasm risk and requires pulmonary function testing before initiation, after 6 months, and annually thereafter.
Automated insulin delivery systems, now the primary method of continuous insulin delivery in type 1 diabetes and guideline recommended for the majority of patients with type 1 and type 2 diabetes, pair an insulin pump, integrated CGM, and control algorithms. Hybrid closed-loop systems still require user-initiated, carbohydrate-matched premeal boluses, and postprandial control can remain suboptimal; fully automated meal-detection approaches have not consistently matched carbohydrate-matched bolusing and may be limited by early postprandial hyperglycemia and late hypoglycemia. Multi-hormone strategies, including insulin-glucagon systems to prevent late postprandial hypoglycemia and insulin-pramlintide approaches that slow gastric emptying and suppress postprandial glucagon, require further technical and safety evaluation. Hypoglycemia remains the shadow over tight postprandial management, with severe episodes reported at 36 to 41 per 100 patient-years in type 1 diabetes and 35 per 100 patient-years in type 2 diabetes; fear of hypoglycemia can drive defensive eating and weight gain. Older adults and those with hypoglycemia unawareness need individualized, less stringent targets. Based on the 2026 ADA Standards of Care, insulin dose adequacy and delivery method should be assessed at every visit and individualized across multiple daily injections, automated insulin delivery, or inhaled insulin, because conquering the mealtime spike demands precision that no single tool yet provides alone.
Subject of Research: Postprandial glucose management in insulin-treated diabetes
Article Title: Postprandial glucose management of people with insulin-treated diabetes
Article References: McGill, J. B., Hirsch, I. B., Levy, C. J., Cengiz, E., Aleppo, G., & Carlson, A. L. (2026). Postprandial glucose management of people with insulin-treated diabetes. Frontiers in Endocrinology, 17, Article 1947837. https://doi.org/10.3389/fendo.2026.1947837
Image Credits: AI Generated
DOI: 10.3389/fendo.2026.1947837
Keywords: diabetes, postprandial glucose, continuous glucose monitoring, automated insulin delivery, inhaled insulin, hypoglycemia, insulin therapy, Postprandial, glucose, management, people, insulin-treated
Cite Scienmag News
Frances Kline. (October 23, 2026). The Mealtime Glucose Problem: Why Postprandial Spikes Defeat Insulin-Treated Diabetes. Scienmag. https://scienmag.com/the-mealtime-glucose-problem-why-postprandial-spikes-defeat-insulin-treated-diabetes/
Frances Kline. "The Mealtime Glucose Problem: Why Postprandial Spikes Defeat Insulin-Treated Diabetes." Scienmag, 23 October 2026, https://scienmag.com/the-mealtime-glucose-problem-why-postprandial-spikes-defeat-insulin-treated-diabetes/. Accessed 23 October 2026.
Frances Kline. "The Mealtime Glucose Problem: Why Postprandial Spikes Defeat Insulin-Treated Diabetes." Scienmag. October 23, 2026. https://scienmag.com/the-mealtime-glucose-problem-why-postprandial-spikes-defeat-insulin-treated-diabetes/