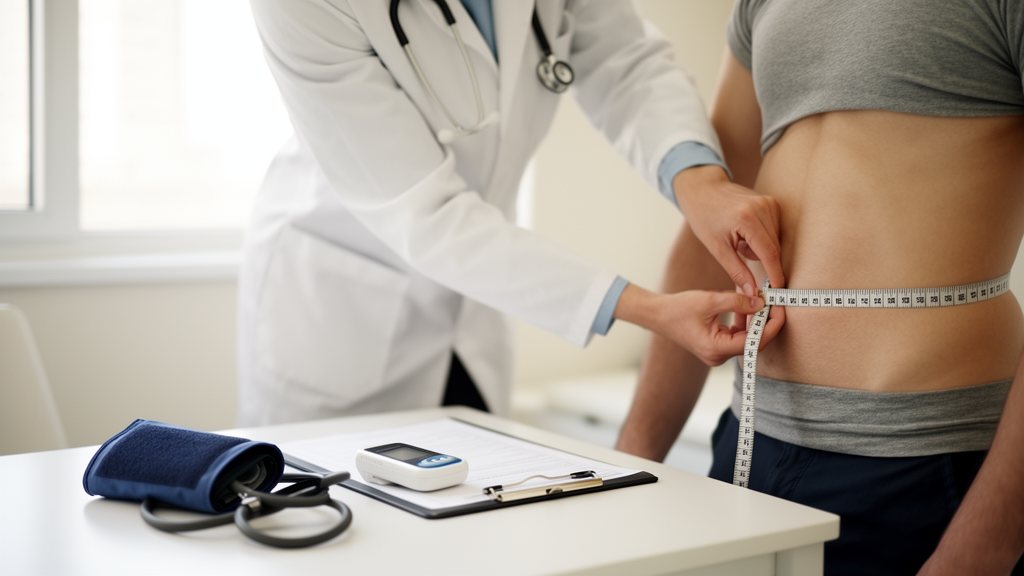
The finding, published in BMC Public Health, indicates that the clinical value of this simple anthropometric metric may depend heavily on a patient's coexisting cardiometabolic conditions rather than applying uniformly across whole populations. In the new study, the investigators combined two independent cross-sectional datasets: 20,261 participants from the Fuqing Cohort Study in China and 6,434 participants from the U.S. National Health and Nutrition Examination Survey (NHANES). Cross-sectional designs capture participants at a single point in time, so the results describe associations rather than proven causal pathways.
The team used multivariable logistic regression to estimate the relationship between BRI and CKD, comparing participants in the highest quarter of BRI values with those in the lowest, and additionally adjusted the models for BMI to ask whether body roundness carried information beyond overall body size. The answer in both cohorts was yes. In the Chinese cohort, people in the top BRI quartile had 1.87 times the odds of CKD compared with those in the bottom quartile after adjustment for BMI, with a 95 percent confidence interval of 1.56 to 2.24.
In the U.S. sample, the corresponding odds ratio was 2.74 (95 percent CI: 1.55 to 4.84). These estimates suggest that where fat is distributed, not just how much of it there is, may matter for kidney health, since the association persisted even after accounting for total adiposity measured by BMI. The most striking result, however, emerged when the researchers stratified the analysis by hypertension and diabetes status.
In the Chinese cohort, the positive BRI-CKD association was statistically significant only in two subgroups: people with both conditions, who had an odds ratio of 1.98 (95 percent CI: 1.42 to 2.75) when comparing the highest with the lowest BRI quartile, and people with hypertension alone, who had an odds ratio of 1.60 (95 percent CI: 1.21 to 2.13). Among participants with diabetes alone, the association essentially disappeared, with an odds ratio of 0.97 (95 percent CI: 0.53 to 1.77), and among those with neither condition the estimate was 1.36 (95 percent CI: 0.95 to 1.93), which did not reach statistical significance. The U.S. data told a compatible but sharper story.
In NHANES, the association between high BRI and CKD was significant only in the subgroup with coexisting hypertension and diabetes, where the odds ratio reached 3.72 (95 percent CI: 1.87 to 7.40). In the other strata of the American sample, the confidence intervals crossed the null value, meaning the data could not rule out no association. The convergence of the two cohorts on the comorbidity subgroup, despite their very different populations and health-care settings, strengthens the case that the BRI-CKD link is genuinely modified by combined hypertension and diabetes.
Because both datasets are cross-sectional, BRI and CKD were measured at the same time, and it is impossible to determine whether higher body roundness preceded kidney dysfunction or whether early kidney disease contributed to altered body composition. The consistency across two large cohorts from different countries nonetheless lends weight to the central observation. For clinicians and public health planners, the practical message is one of targeting rather than universal screening.
The authors conclude that high BRI is associated with increased CKD risk especially in the context of hypertension-diabetes comorbidity, and they argue that this highlights the need for prevention strategies aimed at that subgroup.
Subject of Research: Association of body roundness index with chronic kidney disease modified by hypertension and diabetes comorbidity in Chinese and US cross-sectional cohorts
Article Title: The comorbidity of hypertension and diabetes modifies the association of body roundness index with chronic kidney disease: findings from two cross-sectional studies in China and the US
Article References: Li, X., He, L., Lin, Q., Ni, T., Lin, Z., Liao, X., Chen, J., Qiu, W., Feng, R., Du, S., Li, W., & Ye, W. (2026). The comorbidity of hypertension and diabetes modifies the association of body roundness index with chronic kidney disease: findings from two cross-sectional studies in China and the US. BMC Public Health. https://doi.org/10.1186/s12889-026-29631-z
Image Credits: AI Generated
DOI: 10.1186/s12889-026-29631-z
Keywords: body roundness index, chronic kidney disease, hypertension, diabetes, comorbidity, visceral fat, cross-sectional study, NHANES, Fuqing Cohort Study, BMI, kidney risk, cardiometabolic health
Cite Scienmag News
Jerry Hayes. (October 28, 2026). Body Roundness Index Flags Kidney Disease Risk Mainly in People with Both Hypertension and Diabetes. Scienmag. https://scienmag.com/body-roundness-index-flags-kidney-disease-risk-mainly-in-people-with-both-hypertension-and-diabetes/
Jerry Hayes. "Body Roundness Index Flags Kidney Disease Risk Mainly in People with Both Hypertension and Diabetes." Scienmag, 28 October 2026, https://scienmag.com/body-roundness-index-flags-kidney-disease-risk-mainly-in-people-with-both-hypertension-and-diabetes/. Accessed 29 October 2026.
Jerry Hayes. "Body Roundness Index Flags Kidney Disease Risk Mainly in People with Both Hypertension and Diabetes." Scienmag. October 28, 2026. https://scienmag.com/body-roundness-index-flags-kidney-disease-risk-mainly-in-people-with-both-hypertension-and-diabetes/